



Can Someone Living With Dementia Continue Living at Home? A Guide for Mississauga Families
Yes. Many people living with dementia can continue living at home, particularly in the earlier stages and when the right support is in place. Home is not right for every family, and even where it is, you will come back to the decision more than once. Three things decide it: the stage of the condition, how safe the house is, and how much help is actually in place. This page goes through each one.
Key Takeaways
- Many people with dementia do continue living at home with support, though it is not right for everyone.
- Support usually works best when it starts before a crisis, not after one. The families who manage best tend to add help early.
- Nights are often the first thing to become unmanageable, and often the first thing worth covering.
- A caregiver reaching their limit is a legitimate reason to add support, not a personal failure.
- You can combine publicly funded hours with private hours, and many families do.
- If you do one thing today: call Ontario Health atHome at 1-833-515-1234 to start the assessment process for publicly funded home and community care.
The Short Answer, and What It Depends On
As the Public Health Agency of Canada puts it, “each person experiences dementia and its impacts on daily life differently,” and a person “may still be able to remain active and engaged in [their] work, home life and other responsibilities after getting a diagnosis” (Public Health Agency of Canada, “Dementia: Overview”). The numbers reflect that. In the most recent national figures available, from 2015 and 2016, about 61% of seniors with dementia in Canada were living at home, not in long-term care, with support (Canadian Institute for Health Information, “Dementia in home and community care”).
The honest other half of the answer is that home is not automatically the right place for everyone. Dementia is “a chronic condition that gets more severe over time” (PHAC, “Dementia: Overview”), so the support that keeps someone safe and comfortable has to keep pace.
You are not the only family in Mississauga working through this. There were 119,400 residents aged 65 and over here in 2021, up from 101,785 five years earlier (Statistics Canada, “Focus on Geography Series, 2021 Census: Mississauga (City)”), and across Peel Region the Region projects that one in five residents will be 65 or older by 2041 (Region of Peel, “Peel celebrates Seniors Month,” 2025). Below is what we actually look at with the families who call us.
Factors That Affect Safety and Support
The same diagnosis plays out completely differently in two houses on the same street. A bungalow with a daughter next door is not a two-storey with a spouse who is also unwell. These are the things we look at first. Each one is something to plan around. None of them is a verdict on its own.
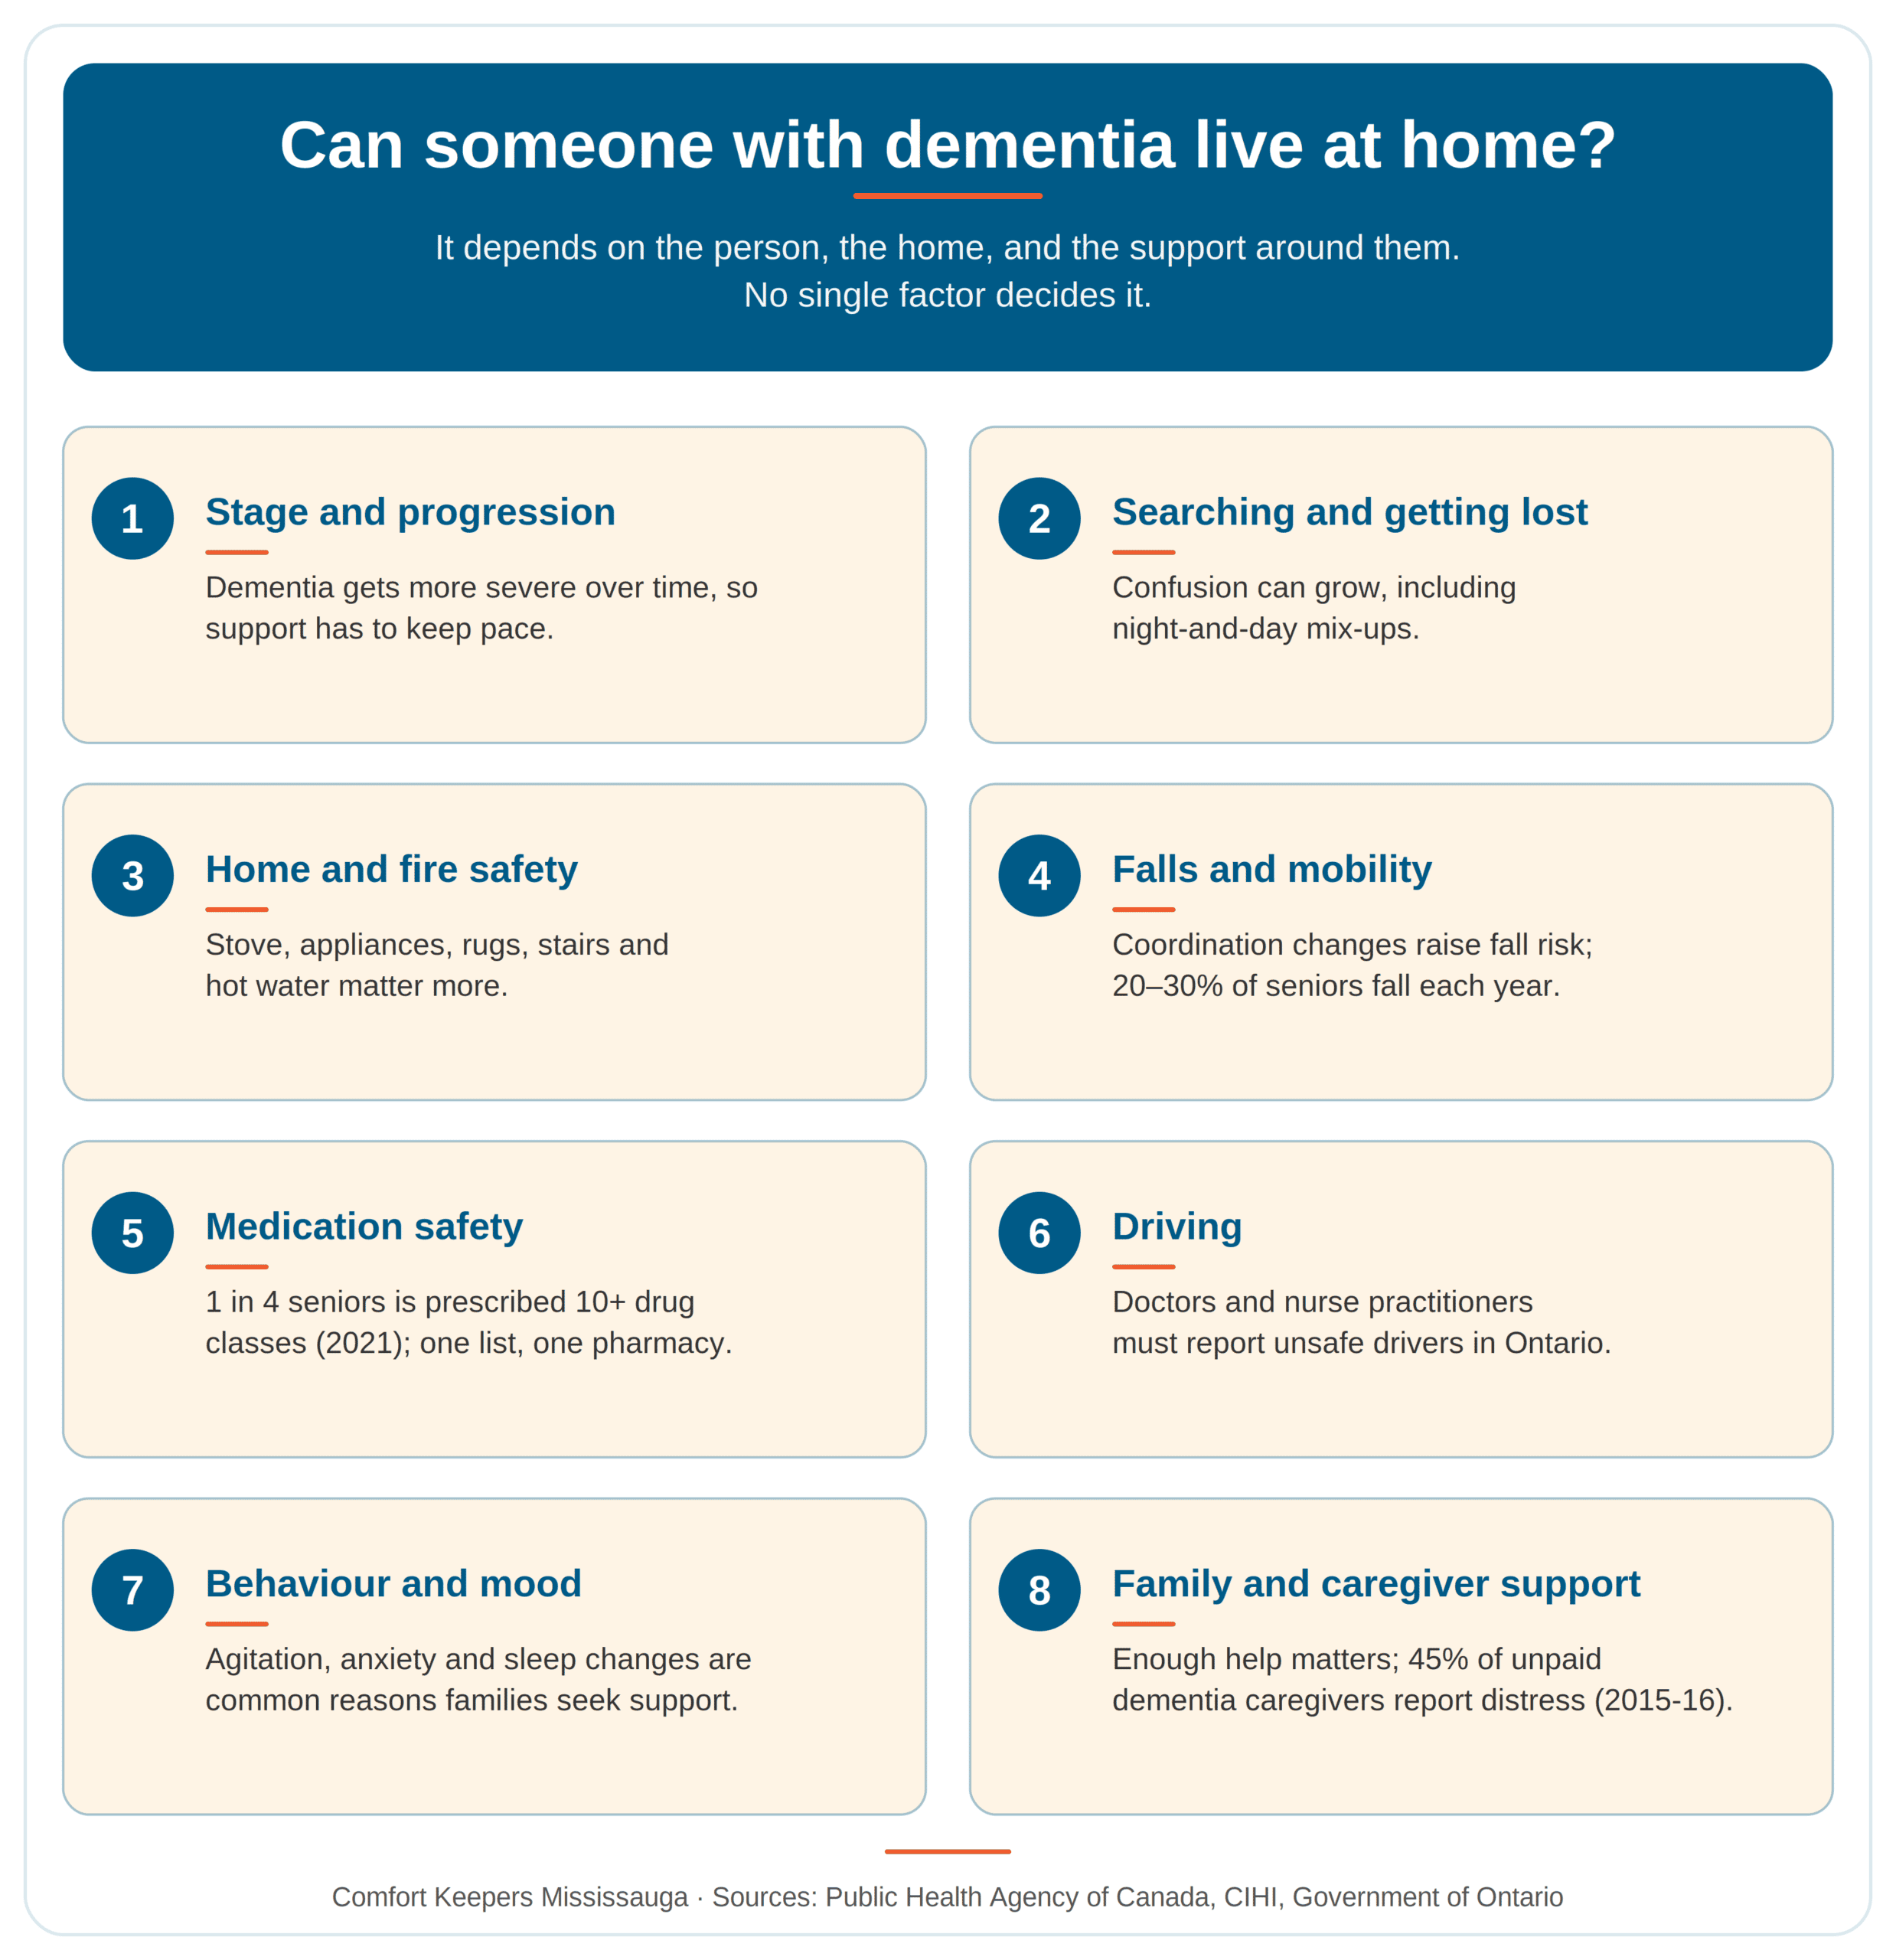
Stage and progression. Early on, help might be light, such as reminders, companionship and a hand with complex tasks. Later, supervision and hands-on personal care usually matter more. The plan that fits this year may not fit next year. That is normal, and not a sign anything has gone wrong.
Searching, wandering and getting lost. PHAC notes that people with more advanced symptoms “may feel confused about where they are as the condition progresses,” which “often leads to searching (sometimes called wandering) or getting lost, even in familiar places” (PHAC, “Dementia: Symptoms and treatment”). Practical things that help: a chime or alarm on the doors so you hear them open, identification on the person, and a recent photograph kept on your phone. Let a couple of trusted neighbours know quietly. If someone does go missing, call 911 right away rather than searching for an hour first. Police would far rather come out and stand down.
Home, kitchen and fire safety. The kitchen is usually where the first real scare happens. The one we hear about most is an element left on, a pot boiled dry, or a smoke alarm taken down because it kept going off. What we suggest first is a stove with an automatic shut-off, and putting the smoke alarm back up. That last one is not optional: by law every home in Ontario must have a working smoke alarm on every storey and outside all sleeping areas (Government of Ontario, “Fire safety in your home”). The general safety basics for seniors apply too: no loose sleeves at the stove, a fire extinguisher mounted away from it, throw rugs secured so they cannot slip, and hot water set to 49°C (120°F). The bathroom and stairs are “particularly hazardous” (PHAC, “The Safe Living Guide: A Guide to Home Safety for Seniors”).
Falls and mobility. Dementia itself can bring “loss of coordination,” “weak and stiff muscles” and “trouble standing, sitting or walking” (PHAC, “Dementia: Overview”), and falls are already the leading cause of injury among older Canadians, with 20 to 30% of seniors falling each year (PHAC, “You CAN Prevent Falls!”). A home that was fine a year ago can become a fall risk as mobility changes.
Medication safety. This is the area where a small slip does the most damage. A missed dose, a doubled dose, or the wrong pill from a sorted tray can put someone in hospital. Below we set out which parts of the medication routine a caregiver can handle and which parts need clinical direction.
Driving. In Ontario, physicians and nurse practitioners have mandatory reporting obligations under section 203 of the Highway Traffic Act when cognitive impairment meets the province’s prescribed reporting criteria, which include substantial limitations in day-to-day functioning. It is a legal duty, not a personal choice. Once a report goes in, the Ministry can suspend or restrict the licence, and there is a process to appeal (Government of Ontario, “Reporting a driver for medical review”). What we tell families: do not make this your fight. Raise it with the family doctor and let the medical process carry the difficult part, so you are not the one who took the keys. Plan for what replaces the car too, because the loss families underestimate is not the driving, it is the independence.
Behaviour and mood changes. You will hear the term “responsive behaviours.” PHAC uses it for things like “agitation, irritability, hallucinations, sleep disruptions” and searching, alongside mood changes such as “anxiety, depression, loss of interest in activities they used to enjoy,” often triggered by feeling “afraid or unsafe” or “overwhelmed or rushed” (PHAC, “Dementia: Symptoms and treatment”). The word “responsive” is the useful part. These are usually a response to something. Someone is in pain, needs the bathroom, is frightened, or is being rushed, and cannot say so. When we get called about behaviour, the first thing we look for is what the behaviour is responding to.
Is it safe for someone with dementia to live alone?
Some people in the earlier stages live alone safely with light support such as check-ins, meal help and reminders. Rather than a yes or a no, here is what we look at when a family asks us this:
- Could they use the phone in an emergency, and would they think to?
- Is food going bad in the fridge, or not being bought at all?
- Has the stove been left on more than once?
- Have they had a fall, or a near miss they did not mention?
- Are they going outside at night?
- Are the bills being paid?
- Do they call you far more often than they used to, or noticeably less?
In our experience, one of these on its own means it is time to add some help. Three or four together means it is time for a proper assessment of whether living alone is still safe. As dementia advances the need for supervision grows, so this is a question worth coming back to.
Daily Routines and Personal Care
Most of what makes home workable day to day is a steady routine plus real hands-on help with everyday tasks. PHAC lists “being in familiar settings (avoid changing the location of objects or furniture in the home),” “keeping an active social life,” “having a variety of activities to take part in” and “meaningful engagement, such as continuing favourite activities” among the approaches “often used before choosing medication” (PHAC, “Dementia: Symptoms and treatment”). In our experience, keeping the day in a person’s own familiar order helps: waking, meals, a walk, the activities they know. When the shape of the day stays the same, they can see what is coming next, and that settles them.
The tasks that slip go in a recognizable order. Complex activities become difficult first. PHAC notes that “familiar tasks such as grocery shopping, cooking, using the television remote, and keeping track of payments may become more challenging” (PHAC, “Dementia: Symptoms and treatment”). In what we see, basic self-care becomes difficult later, as coordination declines: eating, bathing, dressing, using a phone, pouring a drink, managing buttons and zippers. The part families find hardest to watch is that understanding and doing come apart. Your father may know exactly what he wants to do with the shirt in his hands and still not be able to do it.
What tends to change, and how support can help
| Everyday area | What families may notice | How support at home can help |
| Meals and cooking | Grocery shopping and cooking get harder; meals get skipped or become harder to manage | Shared, unhurried meals, grocery and meal prep, and gentle reminders to eat and drink |
| Money and appointments | Trouble keeping track of payments and appointments | Help organizing bills and calendars, plus reminders |
| Bathing and dressing | Difficulty with bathing, dressing, buttons and zippers as coordination declines | Respectful, step-by-step personal care that protects dignity |
| Moving around the home | Trouble standing, walking and moving safely | A safer home setup and a steady hand to help prevent falls |
| Staying engaged | Loss of interest in favourite activities | Familiar routines, company, and activities the person still enjoys |
Meals deserve a mention, because eating often falls off quietly. With dementia the problem is rarely just appetite. Someone may forget they have eaten, or forget that they have not, lose the sequence of using cutlery, or struggle to see food that does not contrast with the plate. Eating with other people helps, and Health Canada notes it “is great for the company and it can also be good for [your] health” (Health Canada, “Healthy eating for seniors”). A shared meal with no rush in it is often one of the calmest parts of the day.
How you speak to someone with dementia changes how the task goes. PHAC’s guidance is to “always assume that a person living with dementia is aware and listening,” to use short sentences “that make one point each,” to “be patient and give time to respond,” to make eye contact, and to avoid raising your voice, which can cause distress (PHAC, “Dementia: Tips on how you can help”). One thing our caregivers do that sounds small: they sit down before they speak, so they are at eye level, not standing over someone. It changes how a bath or a meal goes more than almost anything else. Through all of it, we try to help the person do what they still can for themselves, and not quietly take tasks over.
Medications: What a Caregiver Can Do, and What Needs a Nurse
With dementia care at home, the line between what a non-medical caregiver may do and what needs a nurse or doctor is set by Ontario regulation, not by preference. Two phrases in the official documents are worth knowing. A “regulated health professional” means someone with a licence and a governing college, such as a nurse or a doctor. An “unregulated care provider” is the official term for caregivers and personal support workers. It sounds alarming and it should not. It does not mean untrained or unchecked. It means the profession itself has no licensing college, so responsibility sits with the employer, which is why hiring, screening, training and supervision matter so much.
Here is the short version on medications. Diagnosing, prescribing and clinical decisions stay with the doctor, nurse practitioner and nurses. Most of what a non-medical caregiver does is reminding, opening a blister pack, handing over a dose and recording that it was taken.
It is a common assumption that a caregiver can only ever give reminders. In fact it depends on the task, the caregiver’s training, the individual care plan, and the provider’s policies. Ontario’s own respite-care guidance lists “assistance with medications” among personal support tasks, alongside oral care, bathing and dressing (Government of Ontario, “Respite care”). A nurse can also train a caregiver to give oral medications. Ontario’s nursing college allows it, but only under specific conditions: the person’s health has to be stable and predictable, the caregiver’s competence has to be confirmed, and clear policies and support have to be in place (College of Nurses of Ontario, “Teaching an unregulated care provider”; College of Nurses of Ontario, “Working With Unregulated Care Providers”). All three conditions, not one or two. In practice that means we do not take on a medication task unless it is written into the care plan and a nurse has signed off on it.
Getting this right matters more with dementia, because the medication load is already high. With 1 in 4 seniors prescribed 10 or more drug classes in 2021 (CIHI, “Drug use among seniors in Canada”), a missed or doubled dose is a real risk. PHAC’s advice is to keep one written list that every doctor and pharmacist knows about, and to use a single pharmacy so interactions get caught (PHAC, “The Safe Living Guide: Keeping track of your medicine”).
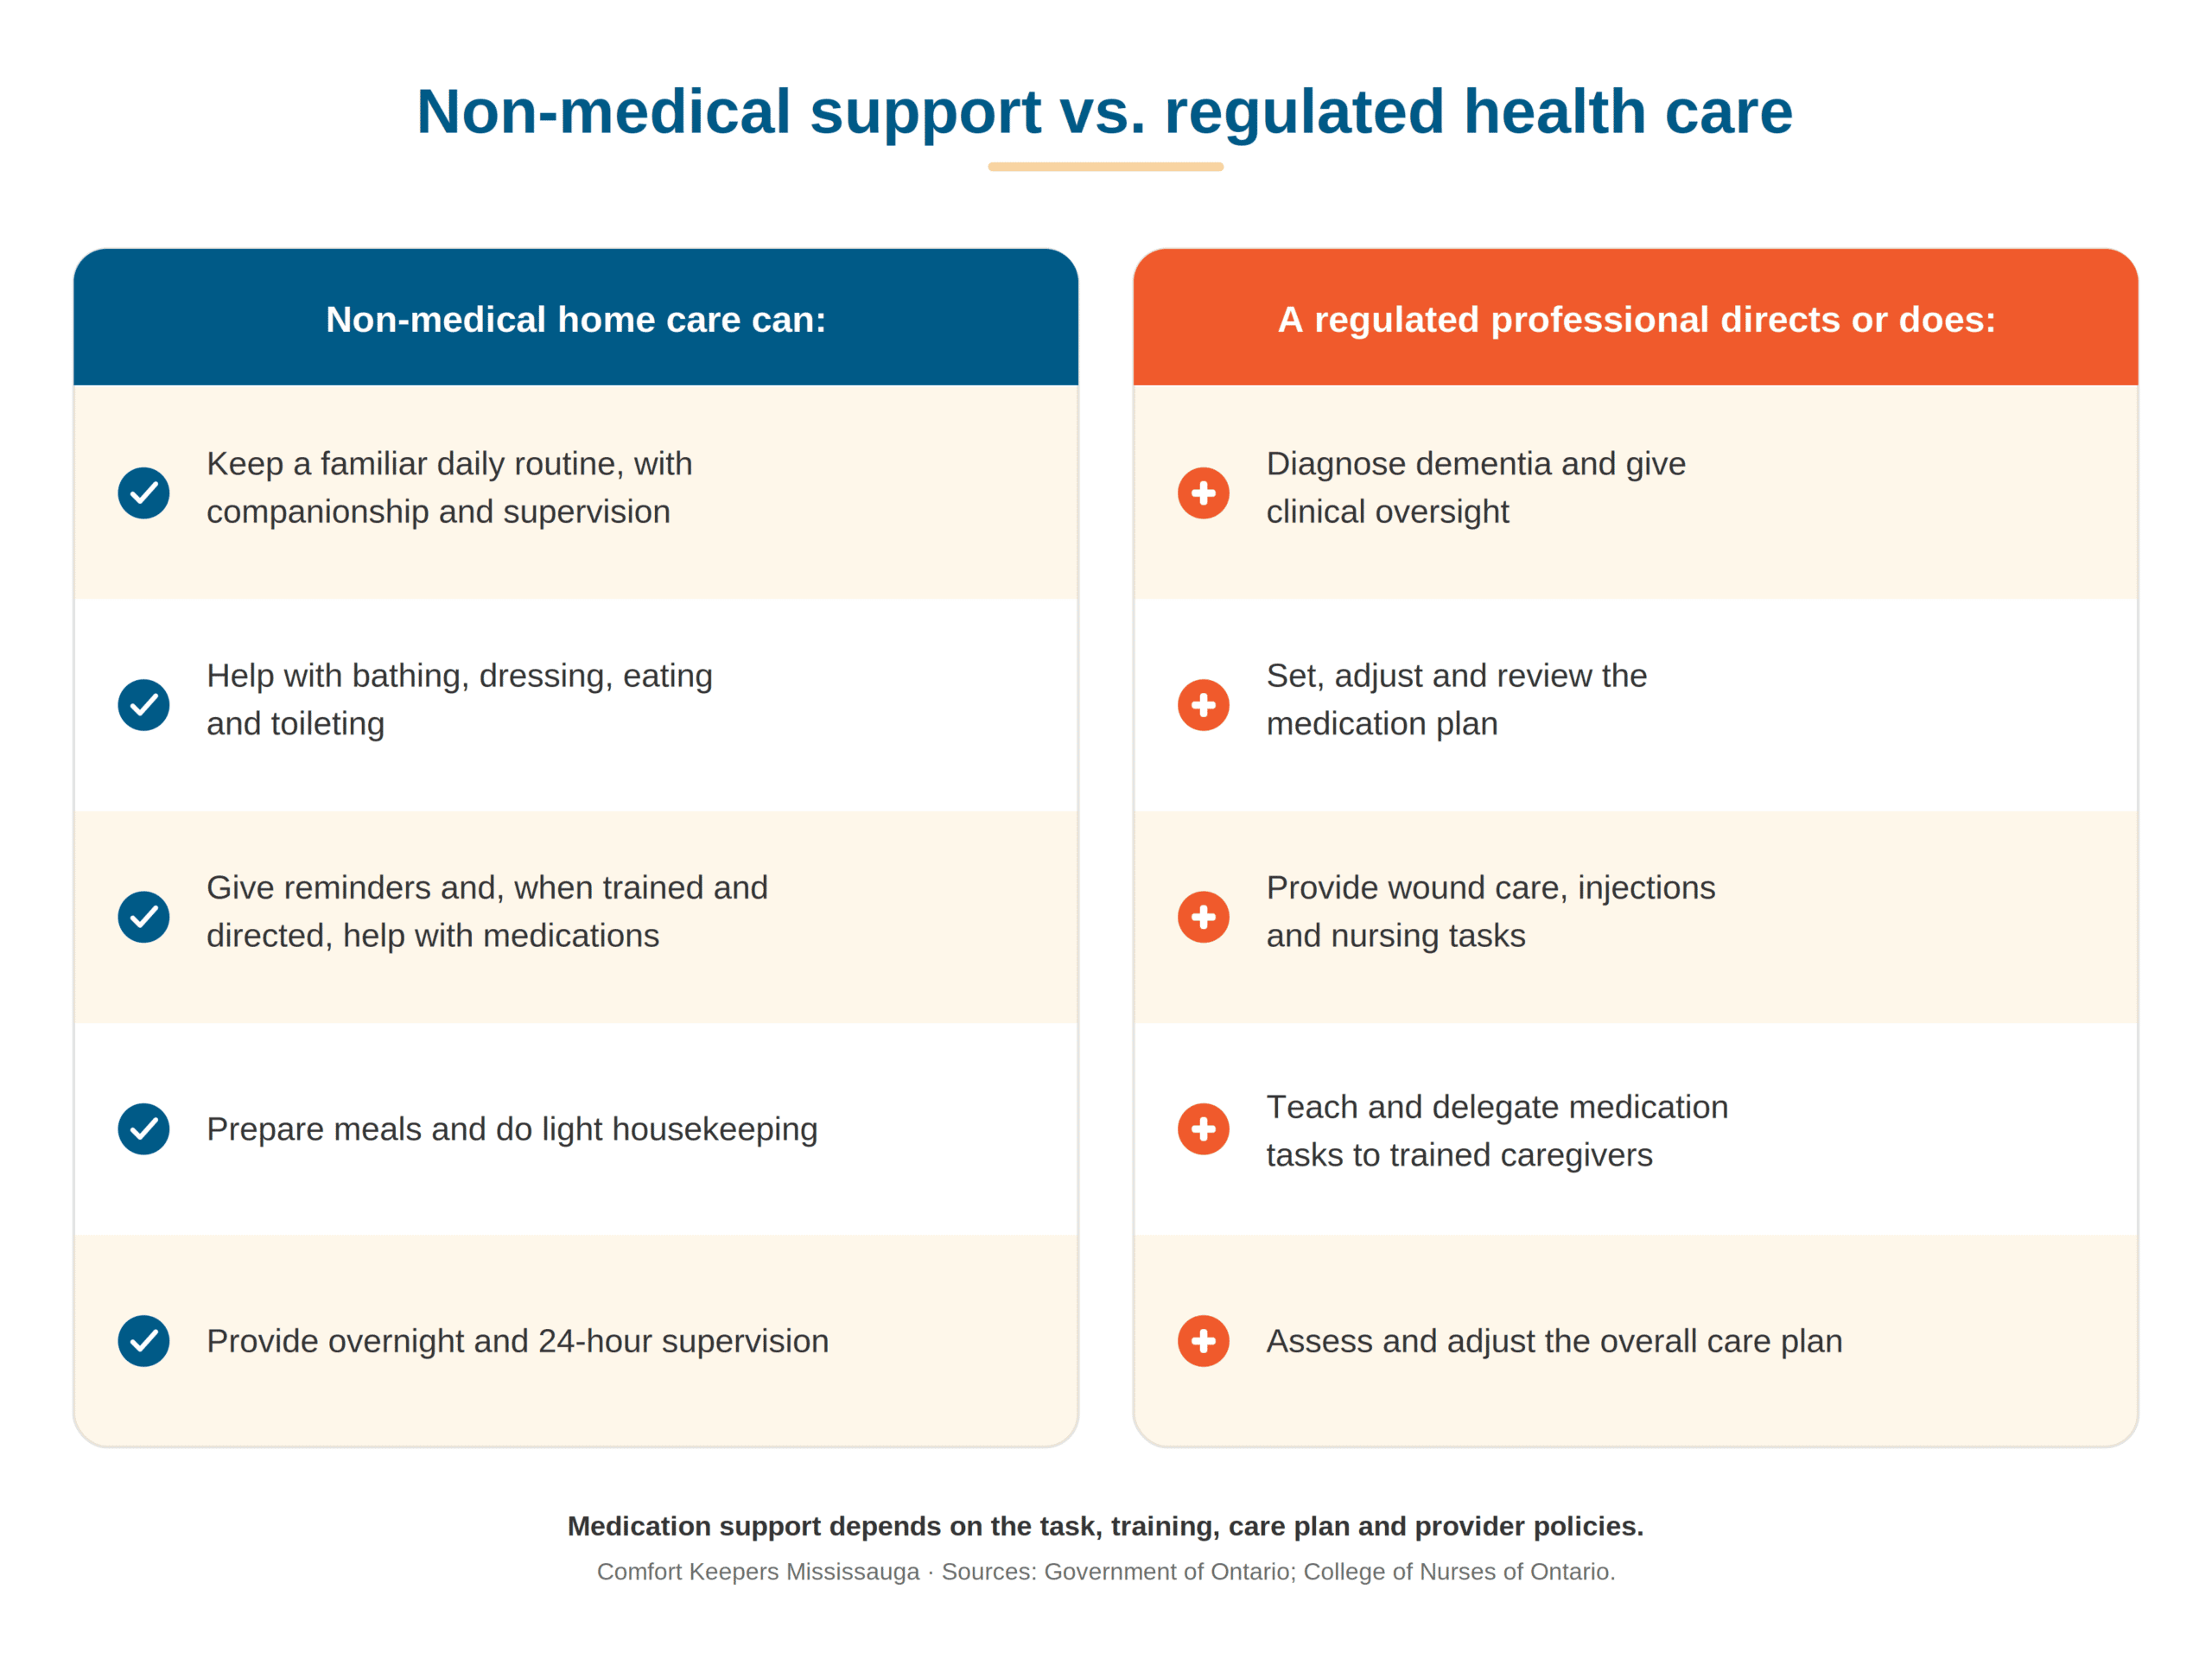
Before a first shift, we sit down with the family, the medication list and whoever is prescribing, and we write on one page who does what: which medications the caregiver hands over, which ones need a nurse, who calls the pharmacy when something changes, and who the family calls at 2 a.m. A copy stays in the home. If you want to know exactly where that line sits for your parent, ask us and we will show you in writing.
Can the Family Caregiver Keep This Up?
Whether home works depends on the family caregiver as much as on the person with dementia, and dementia asks more of caregivers than almost any situation we see. In CIHI’s 2015 and 2016 data, “more than 4 out of 10 caregivers (45%) of seniors with dementia exhibit symptoms of caregiver distress,” almost twice the 26% seen among caregivers of other seniors, and they provided “an average of 26 hours of care each week,” well above the 17 hours for other caregivers (CIHI, “Dementia in Canada: Unpaid caregiver challenges and supports”). Hours matter: unpaid caregivers “providing more than 20 hours of care each week had nearly 3 times higher odds of reporting distress” than those providing 10 hours or less (CIHI, “Dementia in Canada: Unpaid caregiver challenges and supports”).
Worth asking yourself honestly:
- Are you sleeping through the night more than two or three nights a week?
- Have you cancelled your own medical appointments to cover care?
- Is one person carrying this while others help occasionally?
- Could you leave the house for two hours without arranging something first?
- Has your own health changed since you took this on?
Answering badly on most of these does not mean you are failing. It usually means the load has outgrown one person. Often the person carrying it is an adult son or daughter, and caregivers frequently report feeling tired, worried or anxious (Statistics Canada, “The Daily: More than half of women provide care to children and care-dependent adults, 2022”). A caregiver reaching the edge of what they can manage is a valid reason to add support. Reaching that point is human. Bringing in help, even a few hours a week, is often what lets someone keep doing this for another year. Our respite care exists for that reason, so the family caregiver gets a real break while someone they trust is in the house.
Overnight and 24-Hour Support
For a lot of the families we work with, nights are what decides whether home keeps working. When the nights are covered, the days become manageable again. When they are not, exhaustion makes the decision before anyone is ready for it. PHAC recognizes the pattern: “confusion between night and day” is one reason a person may search or wander, “sleep disruptions” are a common responsive behaviour (families often call this sundowning), and dementia “can affect the internal clock that keeps us on a regular eating and sleeping schedule” (PHAC, “Dementia: Symptoms and treatment”). When someone is up, disoriented and moving around the house at 3 a.m., a family that has to work the next day cannot safely carry that alone for long.
Different agencies mean different things by “24-hour care,” so it is worth asking exactly what you are being quoted. What matters is not the label. It is how many hours someone is awake and with your parent, and what happens in the hours nobody is there. Ontario’s own rules recognize a person who needs “constant supervision as a result of a cognitive impairment,” meaning someone who cannot safely be left alone (Government of Ontario, “Home and community care”). Our Mississauga care services include overnight and 24-hour support, built around what actually happens through the night. When someone wakes at 2 a.m. convinced it is morning, our caregiver does not argue. She turns on a light, makes tea, sits for a few minutes, and walks them back to bed once they have settled. Add a hand to the bathroom so a 3 a.m. trip does not end in a fall. Add a night of real sleep for the family. For a lot of households, that is what makes everything else possible.
When Long-Term Care or Another Setting May Be Safer
Another setting, whether a retirement residence or long-term care, becomes worth considering when safety needs outrun what can be arranged at home, and overnight supervision is usually the point where that happens. We should be straightforward with you about something here. We are a home care company, so we have an interest in the answer being home. That is exactly why we try to be careful here. For some families the right and kindest answer is long-term care, and if that is where you are, we will say so and help you get there.
The trigger to reassess is usually safety. Government guidance puts it as a single question: “Is the person’s home safe? If not, contact home care for an in-home assessment.” It also advises looking ahead at home modifications, assisted living and long-term care before you need them, because many housing options have waitlists and only some are publicly funded (Government of Canada, “Care options, choosing the best plan for you and the person you care for”).
In Ontario, long-term care is for people who “require 24-hour nursing care and personal care” and help with everyday things like eating, washing and dressing, and applications are “arranged by Ontario Health atHome organizations” (Government of Ontario, “Explore your care options”; Government of Ontario, “Apply for long-term care”). Because of those waitlists, applying early is worth considering even if you are unsure. There is no fee to apply. Be aware, though, of what happens once you are on a list. When a bed is offered you have 24 hours to accept or decline, and up to five days to move in. If you decline, you are removed from every waiting list you are on and have to wait 12 weeks before reapplying, unless your condition or circumstances change significantly (Government of Ontario, “Apply for long-term care”). It is worth knowing that before you apply, not after. Need and safety decide this, not the date you applied. Often home is still the answer. As Ontario notes, “you may be able to stay in your own home with supports in your community, such as personal support worker visits” (Government of Ontario, “Apply for long-term care”).
When is it no longer safe for someone with dementia to live at home?
No single moment applies to everyone, but a handful of signs appearing together suggest it is time to reassess the setting with the care team:
- Repeated wandering or getting lost, especially away from the home
- Serious home-safety risks that cannot be managed, such as fire or stove hazards
- Frequent falls or injuries
- A need for supervision through the night that no one can safely keep up
- A family caregiver who can no longer keep it up safely
One of these alone is usually a prompt to add support. Several together, or any one that puts the person at immediate risk, is the point to talk seriously with the care team about whether more help at home or a move is the safer choice.
Questions to Ask the Care Team
Questions worth asking, and worth taking with you to an appointment:
- What stage are we looking at, and what changes should we expect next?
- Which tasks need help now, and which are becoming unsafe?
- What here is non-medical support, and what needs a nurse?
- What happens overnight?
- What are the signs it would be time to reassess whether home is still right?
You are not meant to answer these yourself. The family doctor takes the medical ones, the Ontario Health atHome coordinator takes eligibility and hours, and we can answer the day-to-day ones.
Where to turn in Ontario
| Where | Contact | What it is for |
| Ontario Health atHome | 1-833-515-1234 | Province-wide line for a free home-care assessment; routes to the Mississauga Halton office |
| Health811 | 8-1-1 | Free, confidential registered-nurse advice, 24 hours a day |
| Family doctor | Your clinic | Assessing memory concerns, diagnosis and referrals |
| Comfort Keepers Mississauga | (905) 671-4004 | A free care conversation and a practical, adjustable plan at home |
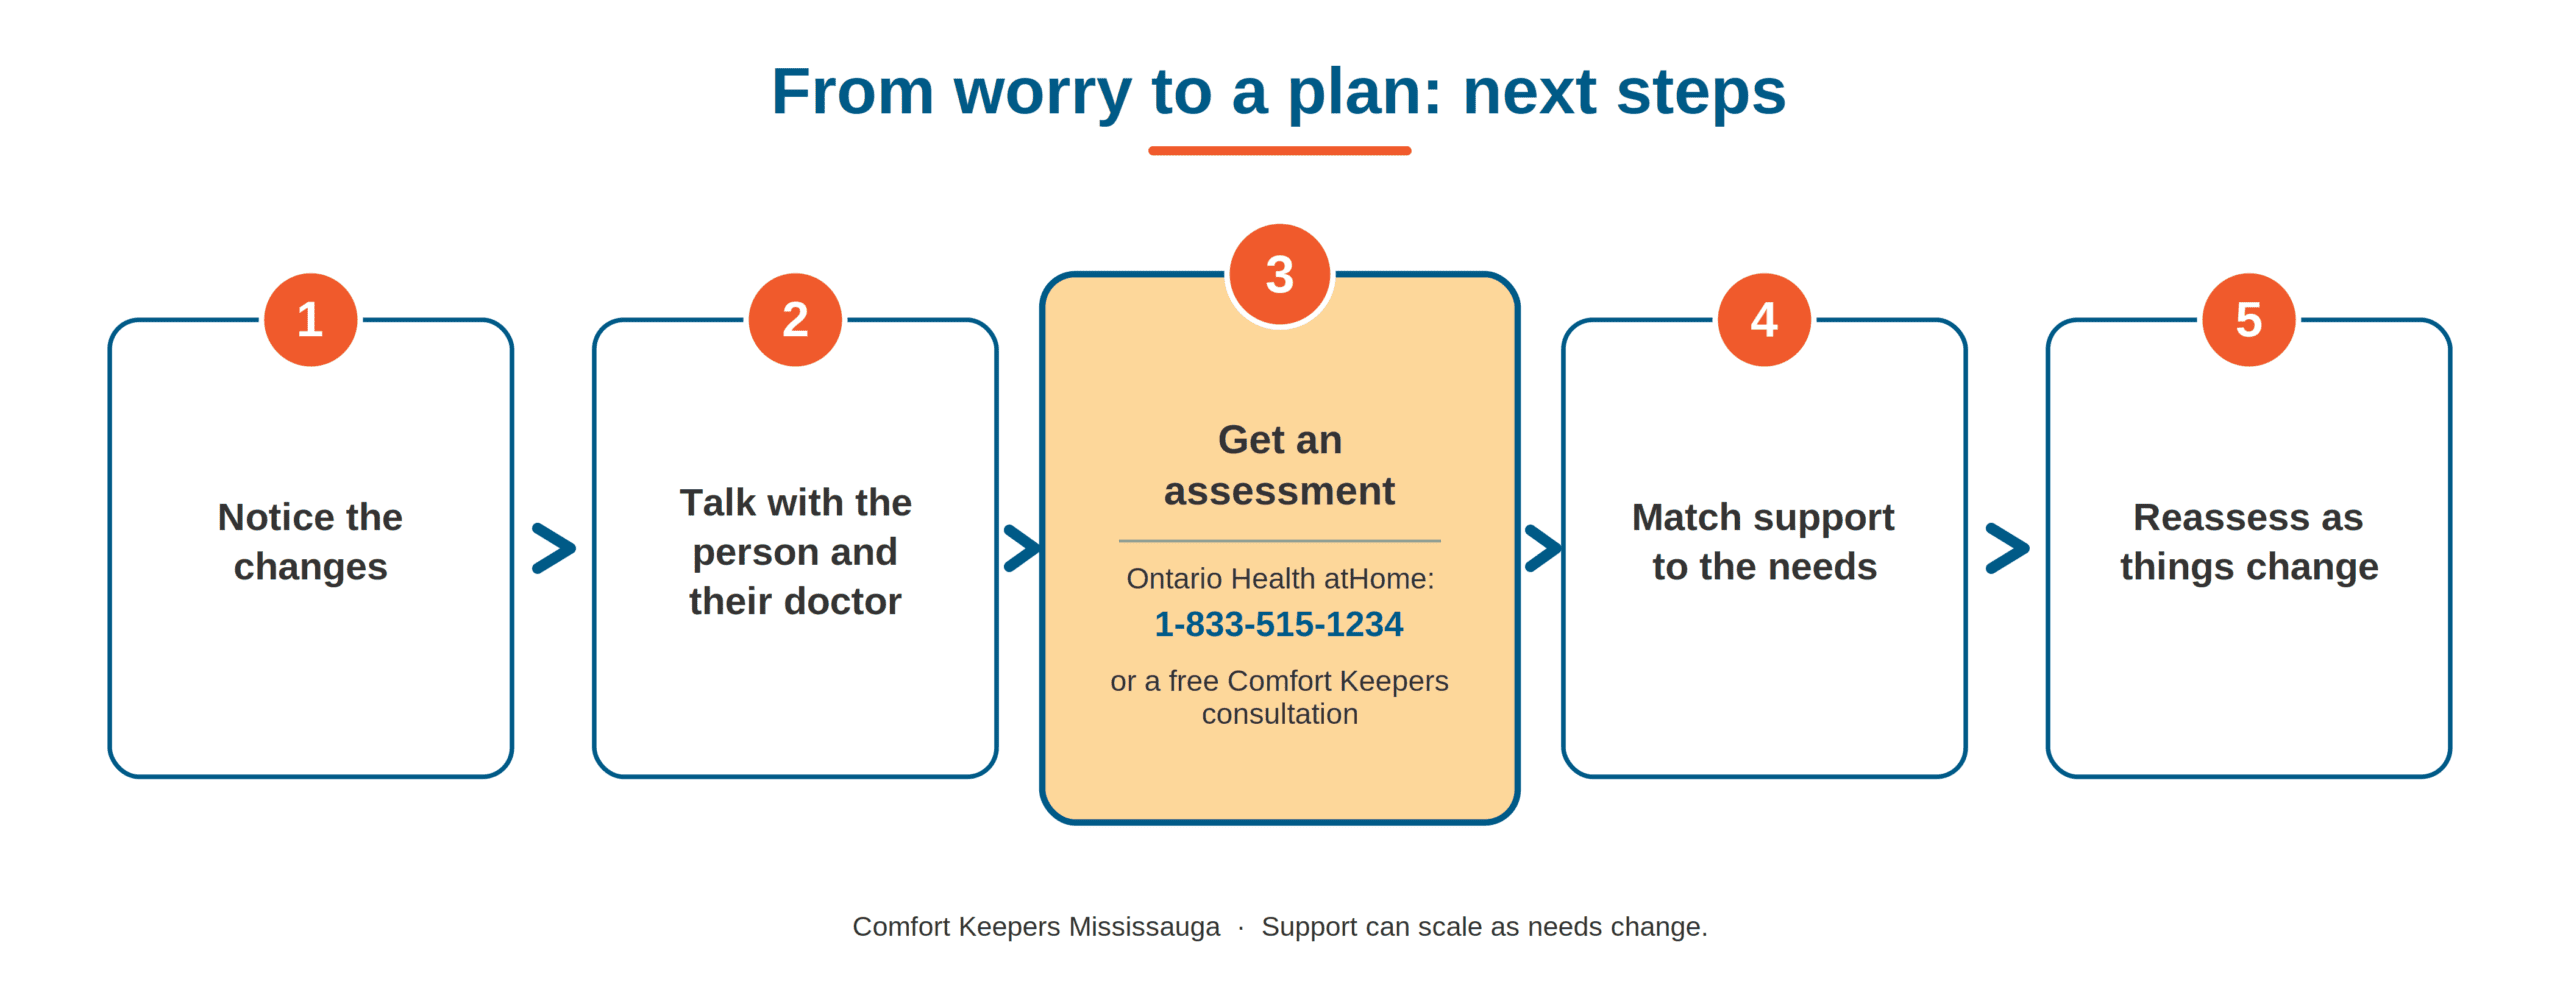
Here is the order we suggest:
- Start with the family doctor if the memory changes have not been assessed yet. Diagnosis and clinical guidance begin there.
- Call Ontario Health atHome at 1-833-515-1234 to start the assessment process for publicly funded home and community care. The call is free and anyone can make the referral. Eligibility and the level of service are decided from the assessment that follows.
- Prepare for the assessment. In our experience it helps to have the medication list, the diagnosis and the family doctor’s name ready, to have the person being assessed there, and to describe the full range of what is happening, including difficult days, overnight problems and tasks the person can no longer manage reliably. People with dementia often present better in a short visit than they function day to day.
- Fill the gaps. Public services rarely cover everything, especially overnights and weekends. Work out what is left, and whether private hours, family time or a mix covers it.
- Reassess as things change. What fits now will not fit forever, and revisiting the plan is normal.
On cost, we will not pretend it does not matter, because for many families it is the deciding factor. Private home care is billed hourly, and overnight or live-in care is arranged differently from hourly visits. Rather than publish a number that goes out of date, we will give you a real figure for your situation on the first call, before you commit to anything.
How do I get a dementia home-care assessment in Ontario?
Call Ontario Health atHome at 1-833-515-1234. The line runs seven days a week, all year, and routes you to the nearest office, which for Mississauga is the Mississauga Halton team (Ontario Health atHome, “Contact us”; Ontario Health atHome, “Mississauga Halton area”). You can call yourself, or ask a family doctor or hospital to make the referral. If you are calling about someone else, they will need to consent, or you will need authority to act for them. A care coordinator, the Ontario Health atHome staff member assigned to the file, then assesses needs and eligibility and may visit the home (Ontario Health atHome, “Home care”). The office serving Mississauga is at 2655 North Sheridan Way, Suite 140 (Ontario Health atHome, “Mississauga Halton area”). For free nurse advice at any hour while you decide, call Health811 at 8-1-1 (Government of Ontario, “Your health”).
Talk to Our Mississauga Care Team
If you are not sure where you are in all this, start with the free call: Ontario Health atHome, 1-833-515-1234. It costs nothing, and it begins the assessment process that determines eligibility for publicly funded home and community care, whatever you decide after that.
When you want to talk through what you are actually seeing at home, we are here for that. We will tell you honestly whether we think home still works, and if the answer is long-term care, we will say so and help you get there.
Ask us about dementia care at home, or reach us through our contact page or by calling (905) 671-4004. We have caregivers from Port Credit and Clarkson through Erin Mills, Streetsville, Meadowvale and Malton, so we can usually tell you on the first call whether we cover the hours you need in your area.
Ask About Dementia Care at Home
About This Article
Last reviewed: August 2026. Author: Comfort Keepers Mississauga. Reviewed by: Brenda Rosati, Director of Operations and Owner. This article is drawn from official Canadian and Ontario sources and reflects our own experience supporting families in Mississauga. It is general information, not medical advice, and it is not a diagnosis. For a diagnosis or clinical guidance, speak with a health-care provider.
About the reviewer.
Brenda Rosati is the Director of Operations and Owner of Comfort Keepers Mississauga, where she leads the local team that supports seniors and their families across Mississauga and reviews the office’s care information for local accuracy. You can read more about our Mississauga office, or reach the team directly.
Sources.
Frequently Asked Questions
Is dementia home care in Ontario publicly funded, or do we pay for it?
Both routes exist. Ontario has publicly funded home care through Ontario Health atHome for people assessed as eligible, covering nursing, personal support (the Ontario term for hands-on help with bathing, dressing, toileting and moving safely) and homemaking (Government of Ontario, “Home and community care”). How many hours someone receives depends on the assessment, and it rarely stretches to ongoing overnight or around-the-clock supervision. Most families we work with use publicly funded hours as the base and add private hours where they help most, often overnights and weekends. When we come into a home that already has public support in place, we build our schedule around it so the two fit together.
Should we sort out power of attorney, and when?
It is worth raising early with a lawyer, because these documents generally have to be signed while the person still understands what they are signing. Families often discover this later than they would like. This is a legal question, not a care one, so we will point you to a lawyer instead of advising on it ourselves. We raise it because waiting can close the door.
What if my parent with dementia refuses help?
This is common, and pushing rarely works. We usually start small and familiar, leading with companionship and a steady routine, not “care,” and letting trust build before adding more. A low-pressure assessment, or a first visit built around something the person enjoys, often opens the door. If you are stuck, talk with our Mississauga team and we will help you find a gentle way in.
